Cannot intubate, cannot oxygenate
Stem
A 46-year-old woman, 118 kg, with no airway history, is induced with propofol and rocuronium 1 mg/kg for an elective laparoscopic cholecystectomy. Three attempts at intubation, including video laryngoscopy and a bougie, fail. Two-handed face-mask ventilation with an oral airway moves no gas, and two second-generation supraglottic airways fail to produce a capnograph trace. Her saturation is 76% and falling, and her heart rate is 52.
Question
What do you do now?
Ideal answer
HeadlineThis is cannot intubate, cannot oxygenate. I name it, call for help and the front-of-neck kit, and do a scalpel-bougie-tube cricothyrotomy now.
- 100% oxygen through whatever is in place; confirm full paralysis. Intubation, two-hand mask and supraglottic oxygenation failed, saturation falling: only the neck remains.
- Vertical midline incision as my default in her habitus, after a laryngeal handshake; up to 8 cm, then blunt finger dissection to the membrane; a transverse stab alone only if clearly palpable or ultrasound-marked.1
- Blade through the membrane, turn, bougie, 6.0 tube: number 10 blade, cuffed tube railroaded over the bougie, cuff inflated, capnography confirms.1
- No pause for sugammadex, because reversal takes minutes and does not guarantee a patent airway.2,1
- Once she oxygenates, treat the bradycardia. Then stabilize her, plan the definitive airway with the surgeon and ICU care, document and disclose.
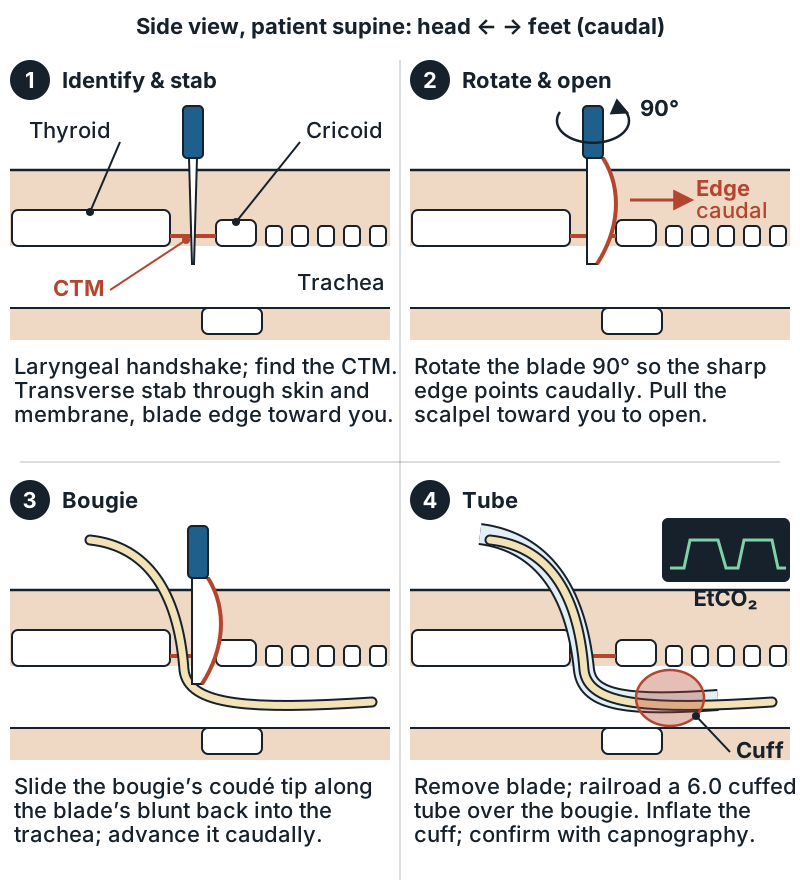
Breaking down the answer
- Declare it early — the trigger is failed oxygenation, not a number; at a displayed 80% the real value is lower and falling. Naming it turns a crowd into a team with one task; the candidate who tries one more blade fails on judgment (adaptability, organization).
- Limited attempts at each rescue — optimized two-handed face mask, oral airway, full relaxation; supraglottic airway at most three attempts, two with my preferred second-generation device and one alternative.2 Changes if a supraglottic airway oxygenates: I stop and think; this is no longer CICO.2,1
- Why paralysis — an unparalyzed, partially obstructed patient is the hardest airway; relaxation removes laryngospasm and chest wall rigidity. Full block before critical hypoxia is the last chance to rescue without cutting,2 and the neck is never cut without it.1
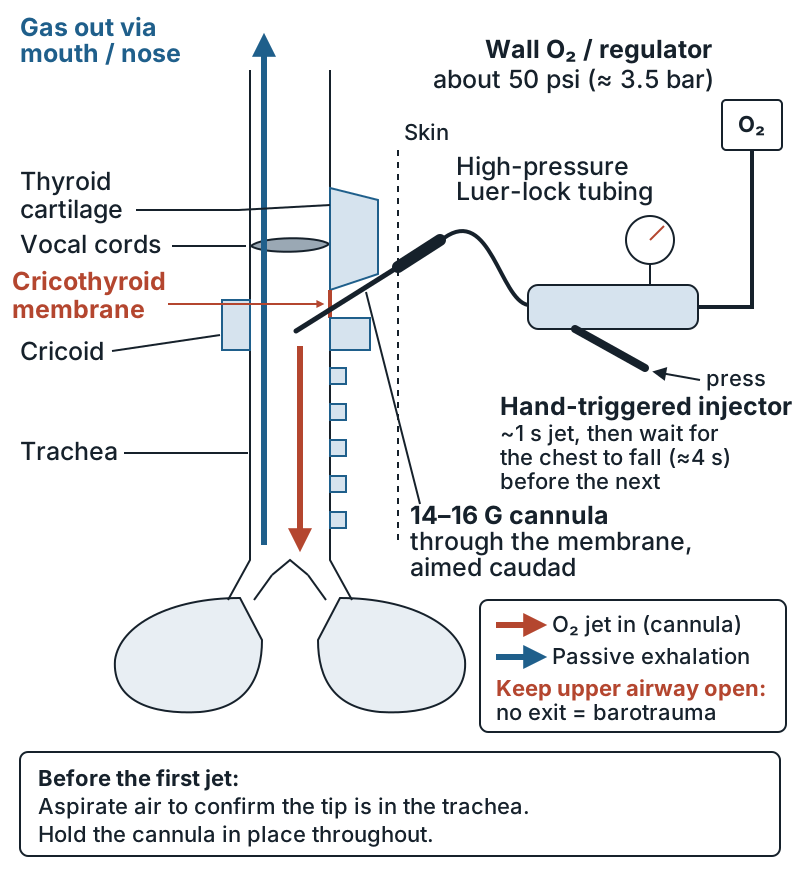
- Scalpel over needle — a cuffed wide-bore tube allows normal ventilation via a standard circuit; high-pressure oxygenation through a narrow cannula carries serious morbidity.2 Only in a child aged 1–8,3 membrane too small for a blade: needle cricothyrotomy with jet ventilation, barotrauma accepted.
- Sugammadex is not a rescue — 16 mg/kg is the labeled dose soon after rocuronium 1.2 mg/kg,4 but an obstructed patient gains nothing from returning drive. I name it and reject it.
- What I would do differently — predicted difficulty with both intubation and mask ventilation means an awake technique; the strongest answer closes by saying so.
Follow-up question
You place the tube through the neck, but the chest does not rise, there is no capnograph trace, and the neck is swelling. What now?
Follow-up answer
HeadlineA false passage: no end-tidal CO2 within two breaths, no chest rise, a swelling neck. I stop ventilating through it and tell the room.
Every breath into the tissues makes the next attempt harder, so I move to an alternative invasive technique, as the guideline expects.5 If the surgeon is present, they convert to an open tracheostomy while I keep trying to oxygenate from above with a supraglottic airway and two-handed mask. Alone, I extend the incision, re-identify the trachea by finger and place the bougie under direct vision. If she arrests from hypoxia, ACLS with the airway as the reversible cause, continuing the surgical airway during compressions and reassessing with capnography.
Pitfalls that cost points
- Repeating laryngoscopy a third and fourth time because "the view was almost there."
- Choosing needle cricothyrotomy in an adult and then being unable to explain how the patient exhales.
Rapid-fire
Q: Why the cricothyroid membrane and not the trachea? A: It is superficial, midline, relatively avascular and bounded by cartilage; a tracheotomy through the thyroid isthmus bleeds and takes minutes I do not have.
Q: Why does a supraglottic airway so often rescue a failed mask? A: It bypasses the tongue and soft palate, the usual sites of obstruction, and seals below them; it fails when the obstruction is at or below the glottis.
Q: How does the patient exhale after needle cricothyrotomy? A: Only through the native upper airway; if that is completely obstructed, each jet stacks and causes barotrauma within minutes, which is why I convert to a surgical airway.
Q: When do you wake the patient instead of cutting? A: Only if I can oxygenate; waking is an option after failed intubation with successful ventilation, never in CICO.
Numbers to know
| Item | Value |
|---|---|
| Supraglottic airway attempts | Maximum 32 |
| Scalpel | Number 10 blade, transverse stab, rotate 90° |
| Tube through cricothyrotomy | 6.0 cuffed, railroaded over bougie2 |
| Vertical midline incision | Up to 8 cm; the default unless the membrane is clearly palpable or ultrasound-marked1 |
| Needle cricothyrotomy | Children aged 1–8 years only;3 jet 1 s on, 4 s off |
| Sugammadex for rocuronium rescue | 16 mg/kg;4 does not guarantee airway patency, not a CICO plan |
Links
- Anticipated difficult airway and the ASA algorithm, Awake fiberoptic intubation: topicalization and sedation, laryngospasm, Tracheostomy, laser surgery and jet ventilation, sugammadex, Hypoxic gas mixture and oxygen supply failure
- Atlas: Capnography: waveforms and sudden loss of ETCO2; Monitor atlas: perioperative respiratory events
- ASA Practice Guidelines for Management of the Difficult Airway (2022); Difficult Airway Society guidelines for unanticipated difficult intubation in adults
Sources
- 1.Difficult Airway Society 2025 guidelines for management of unanticipated difficult tracheal intubation in adults · DAS, 2025 · sea.org.ecAhmad et al., Br J Anaesth 2026;136:283-307 (online 7 Nov 2025), doi 10.1016/j.bja.2025.10.006; full English text hosted by the Sociedad Ecuatoriana de Anestesiología. Replaces DAS 2015 for attempts, eFONA technique (vertical incision default) and sugammadex.
- 2.Difficult Airway Society 2015 guidelines for management of unanticipated difficult intubation in adults · DAS, 2015 · ebi.ac.ukFull text via Europe PMC (PMC4650961); Plan B-D and scalpel-bougie-tube technique. Superseded by DAS 2025 for the eFONA incision and attempt limits.
- 3.Paediatric difficult airway guidelines · APA / DAS · das.uk.comHosts the APA/DAS algorithms for children aged 1 to 8 years, including cannot intubate and cannot ventilate (CICV) in a paralysed anaesthetised child; the CICV PDF itself could not be downloaded (server error), so only the age band is cited.
- 4.BRIDION (sugammadex) injection prescribing information · FDA / DailyMed · dailymed.nlm.nih.gov
- 5.2022 American Society of Anesthesiologists Practice Guidelines for Management of the Difficult Airway · ASA, 2022 · asa2.silverchair.com
Facts on this page were checked against these sources on Oct 14, 2026. Guidelines change; confirm doses against current institutional protocols.