Pneumothorax and tension pneumothorax
Stem
A 61-year-old man, 88 kg, with emphysema, is undergoing a laparoscopic right hemicolectomy under general anesthesia. A right internal jugular line was placed after induction with two needle passes. Forty minutes in, peak airway pressure rises from 24 to 41 cmH2O, SpO2 falls to 86%, and blood pressure drops to 74/40 with a heart rate of 128.
Question
What is your differential, and how will you manage this?
Ideal answer
HeadlineTension pneumothorax until proven otherwise after a line attempt in emphysema. It is a clinical diagnosis, so unstable means no waiting for a radiograph.1
- Help, 100% oxygen, nitrous oxide off, desufflation, while I listen for unilateral loss of breath sounds and check the tube.
- The differential as I act: capnothorax, bronchospasm, a kinked or endobronchial tube, and anaphylaxis, because each needs a different fix.
- Lung ultrasound only if it takes seconds: absent lung sliding and a lung point.1
- 14-gauge, 8 cm catheter, fourth or fifth space, just anterior to the mid-axillary line, the ATLS site, or the second space at the midclavicular line.2
- Finger thoracostomy or chest tube immediately after, because needle decompression often kinks or fails and I am still ventilating with positive pressure;1 then I reassess and look for a second cause.
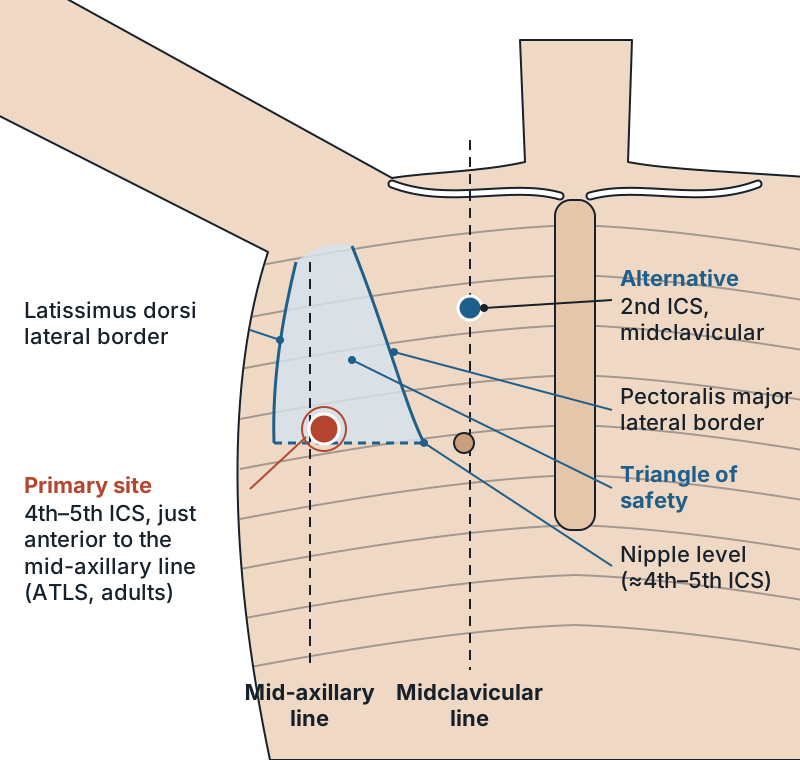
Breaking down the answer
- Clinical diagnosis when unstable — positive pressure turns a small pneumothorax into a tension pneumothorax within minutes, and obstructed venous return kills before imaging. Under anesthesia: rising airway pressure, falling SpO2 and tidal volume, then hypotension and tachycardia; tracheal deviation and distended neck veins come late.
- Why that site — ATLS now favors the fourth or fifth space in adults because an 8 cm catheter there reaches the pleura in more than 90%;2 the second space remains acceptable, especially in children.
- Chest tube follows — a needle converts tension to simple pneumothorax but does not drain it.1 Changes if: a small, stable pneumothorax breathing spontaneously, which I observe with oxygen; trauma before positive pressure, where I ask for a chest tube first.
- Stop nitrous oxide — it is about 30 times more soluble in blood than nitrogen, so it enters the air space faster than nitrogen can leave;3 in Eger's classic study a pneumothorax doubled in 10 minutes.4
- Ultrasound beats the supine film — 94% sensitive and 100% specific in skilled hands.1 Absent B-lines add to absent sliding; sliding at the anterior chest excludes it at that point.
- Recognize the setting — a subclavian or internal jugular attempt, supraclavicular or paravertebral block, rib fractures, bullous disease, high-pressure ventilation, surgery near the diaphragm such as nephrectomy or upper abdominal laparoscopy; the stem usually plants one.
- Capnothorax in laparoscopy — CO2 through a diaphragmatic defect raises airway pressure and end-tidal CO2; it often resolves with desufflation and PEEP because CO2 absorbs quickly, and needs drainage only if it causes instability.
Follow-up question
You decompress the right side with a needle and hear a rush of air, but two minutes later his blood pressure is 60/40 and his SpO2 82%.
What now?
Follow-up answer
HeadlinePersistent obstructive shock after decompression; I say it to the team and ask for an immediate finger thoracostomy and chest tube on the right.
I check that my catheter has not kinked or dislodged. If he still does not recover, I examine and scan the left side and decompress it if sliding is absent, because his emphysematous lung sees the same positive pressure, and I look with ultrasound for tamponade from the line and for hemorrhage while blood is called for. After the tube, a large, persistent air leak or a lung that will not re-expand suggests a major airway injury, needing bronchoscopy and lung isolation. Tidal volumes and pressures stay low until it is controlled.
Pitfalls that cost points
- Forgetting bilateral pneumothorax after bilateral line attempts or blocks.
- Continuing nitrous oxide.
Rapid-fire
Q: Why is the supine chest radiograph insensitive? A: Air collects anteriorly and medially, so the classic apical edge is absent; the deep sulcus sign is subtle.
Q: Why does a tension pneumothorax cause hypotension? A: Rising pleural pressure compresses the vena cava and the heart, reducing venous return, and shifts the mediastinum.
Q: Which blocks risk pneumothorax? A: Supraclavicular, infraclavicular, intercostal and paravertebral blocks; ultrasound reduces but does not eliminate the risk.
Q: What does M-mode show in a pneumothorax? A: A barcode or stratosphere sign, parallel lines throughout, instead of the seashore pattern of sliding lung.
Numbers to know
| Item | Value |
|---|---|
| Decompression catheter | 14-gauge, 8 cm or longer in adults1 |
| Adult site, ATLS 10th | 4th–5th ICS, just anterior to the mid-axillary line2 |
| Alternative site | 2nd ICS, midclavicular line |
| Nitrous oxide solubility | ~30× nitrogen3 |
| Pneumothorax with nitrous | Doubled in 10 min (Eger 1965)4 |
| Ultrasound | 94% sensitive, 100% specific; lung point confirms1 |
Links
- Central venous access and its complications, laparoscopy, Trauma: initial management and damage control, Interscalene block and its complications, Intraoperative hypotension: differential and management
- Atlas: Lung ultrasound: pleura, A/B-lines, effusion, pneumothorax; Monitor atlas: perioperative respiratory events
- ACS Advanced Trauma Life Support (ATLS), 10th edition
Sources
- 1.Tension Pneumothorax · StatPearls · ncbi.nlm.nih.gov
- 2.Needle decompression in tension pneumothorax: anterior or lateral approach? · Journal of Paramedic Practice, 2021 · paramedicpractice.comSecondary summary of ATLS 10th edition (fifth ICS just anterior to the mid-axillary line; 8 cm catheter succeeds in more than 90%); the ATLS manual itself is not openly available.
- 3.Nitrous oxide · OpenAnesthesia · openanesthesia.org
- 4.Is Nitrous Oxide Safe for use in Pneumothorax? · BestBETs · bestbets.orgSummarizes Eger and Saidman 1965 (three ventilated dogs): pneumothorax volume rose 100% in 10 min and almost 300% by 60 min.
Facts on this page were checked against these sources on Oct 14, 2026. Guidelines change; confirm doses against current institutional protocols.