Neuraxial anesthesia for cesarean: epidural top-up, failed block and conversion
Stem
A 31-year-old G1 at 40 weeks, 88 kg, BMI 34, has labored for 11 hours with an epidural infusion of dilute bupivacaine and fentanyl. You have already given two top-ups for left-sided breakthrough pain. She has arrested at 7 cm, and the fetal heart rate now shows recurrent late decelerations with minimal variability. The obstetrician books a category 2 cesarean and wants her in the room in ten minutes.
Question
How will you provide anesthesia for this cesarean?
Ideal answer
HeadlineTwo rescue top-ups make this catheter suspect. I start the top-up in the labor room and decide early: a solid bilateral block, or I resite.
- Extend now: 2% lidocaine, epinephrine, bicarbonate, about 1 mL of 8.4% per 10 mL, 15–20 mL in increments, with fentanyl 100 mcg.1,2
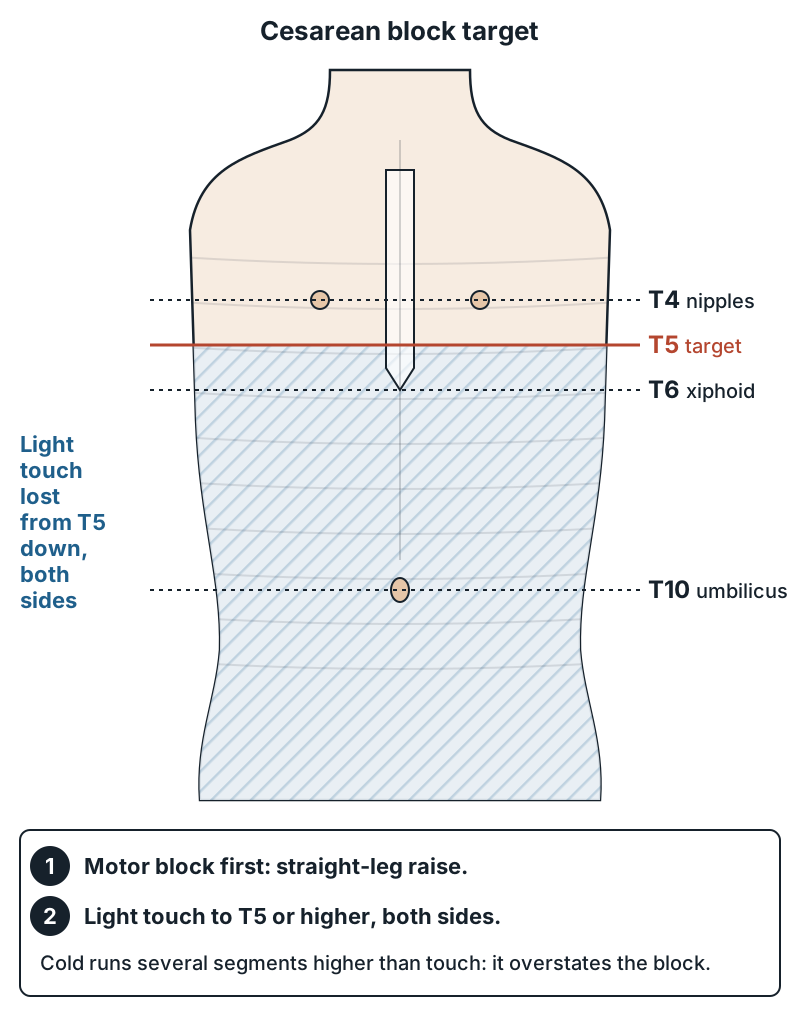
- Test: motor block, then light touch to T5, or higher, bilaterally, before any forceps test.3,4
- Patchy at 10 minutes: reduced-dose spinal or CSE, about 10 mg hyperbaric bupivacaine, opioid omitted, because residual epidural drug risks a high block;4 general if time runs out.
- Phenylephrine infusion and left uterine displacement, holding systolic at 90% of baseline.5
- Neuraxial morphine, epidural 3 mg or intrathecal 100 mcg, with respiratory checks set by dose.6
Watch for: pain at any stage, a rising block, and the tracing, which sets how long I can wait.
Breaking down the answer
- Catheter or fresh block — failed conversion is predicted by urgency (odds ratio 40.4), a non-obstetric anesthesiologist (4.6) and two or more clinician top-ups (3.2).7 Changes if: category 1 with no time; I extend en route, general if it fails.
- Solution choice — chloroprocaine 3% and alkalinized lidocaine are fastest.8 Plain lidocaine-epinephrine takes 10–15 minutes; bicarbonate cut time to T6 from 9.7 to 5.2 minutes.1 Changes if: chloroprocaine may antagonize epidural opioid, so lidocaine when morphine follows.8
- How I test — straight-leg raise first, because a sensory level means nothing without some motor block; repeated cold questioning gives false positives.4 Changes if: the block is one-sided after a full dose; I resite rather than chase it.
- Second neuraxial dose — the 10 mg evidence comes from repeat spinals after partial spinal failure, where 10 mg was safer than 12 mg;4 I extrapolate it to a failed epidural. Changes if: little epidural drug went in; a normal dose.
- Morphine sets monitoring — low dose (intrathecal ≤150 mcg, epidural ≤3 mg) means respiratory rate and sedation every 2 hours for 12 hours; higher doses follow ASA/ASRA hourly checks.6 Changes if: magnesium, sleep apnea, BMI ≥40, IV opioids or sedatives during the case.
- Urgency categories — category 1 is an immediate threat to life (decision-to-delivery 30 minutes or less), category 2 compromise without immediate threat (75 minutes or less).2 Changes if: category 1 with a working catheter; extension still beats an unplanned general.
Follow-up question
The block tests to T5 on both sides. After delivery, as the surgeon exteriorizes the uterus, she cries out that she can feel everything and the pain is severe. What do you do?
Follow-up answer
HeadlineThis is an inadequate block and I believe her; I ask the surgeon to pause and tell her I am treating it now.
The surgeon stops stimulating and returns the uterus.4 I check the level, then give IV boluses of fentanyl 25–50 mcg, remifentanil 20 mcg or alfentanil 250–500 mcg, with ketamine 10 mg or nitrous oxide, never a hypnotic alone.4 I ask for local infiltration. If she still hurts, I offer general anesthesia and convert by rapid sequence with my airway plan ready.9 Afterward I document, debrief and visit her, because dismissed pain causes psychological harm.9
Pitfalls that cost points
- Calling pain "pressure" and sedating her with midazolam.
- Trusting a cold level alone: cold often runs several dermatomes above touch, so it overstates the block.3
- Treating pain before delivery with opioids alone: conversion to general should come early then.
Rapid-fire
Q: Why does bicarbonate speed lidocaine? A: It raises the pH from about 3.4 in commercial lidocaine-epinephrine to about 7.1, so more drug is un-ionized base that crosses the nerve membrane.1
Q: How often does a spinal for cesarean fail? A: About 2.1% need repeat anesthesia within an hour; including supplementation, about 4.1%.4
Q: What conversion-to-general rates are acceptable? A: The Royal College benchmark is under 1% for elective and under 5% for category 2–3 cesareans.4
Q: When does respiratory depression from neuraxial morphine peak? A: Delayed depression peaks about 6.5–7.5 hours after the dose; none has been reported beyond 12 hours at clinical doses.6
Q: Does she need continuous pulse oximetry after low-dose morphine? A: Not routinely; SOAP reserves it for higher doses or added risk.6
Numbers to know
| Item | Value |
|---|---|
| Lidocaine 2% with epinephrine extension | 15–20 mL; onset 10–15 min, ~5 min alkalinized1 |
| Required block | Motor block; light touch to T5 or higher, bilateral3 |
| Failed-conversion risk | Urgency OR 40.4; ≥2 top-ups OR 3.27 |
| IV rescue | Fentanyl 25–50 mcg; ketamine 10 mg4 |
| Low-dose morphine monitoring | RR and sedation every 2 h for 12 h6 |
| Category 1 / 2 delivery target | ≤30 / ≤75 min2 |
Links
- Spinal anesthesia: dosing, spread, hypotension, Neuraxial labor analgesia and its complications, General anesthesia for cesarean delivery, High or total spinal, Fetal heart rate tracings and emergent delivery
- Atlas: Monitor atlas: quantitative NMB and fetal heart rate (2026)
- SOAP neuraxial morphine monitoring consensus (2019); international consensus on vasopressors for spinal cesarean (2018); ASA statement on pain during cesarean delivery (2023)
Sources
- 1.Quick Epidural Top-up with Alkalinized Lidocaine for emergent caesarean delivery (QETAL): trial protocol · Trials (Lechat et al.), 2023 · trialsjournal.biomedcentral.comBackground cites SFAR recommendation of 15-20 mL 2% lidocaine with epinephrine, onset 10-15 min; bicarbonate cut time to T6 from 9.7 to 5.2 min (Lam); Reschke 2020 meta-analysis ranks alkalinized lidocaine fastest.
- 2.Caesarean delivery · NYSORA · nysora.comUrgency categories and decision-to-delivery targets; top-up in 5-10 mL aliquots with fentanyl 100 mcg.
- 3.Prevention and management of intra-operative pain during caesarean section under neuraxial anaesthesia: a technical and interpersonal approach · Obstetric Anaesthetists' Association (Plaat, Stanford, Lucas et al., Anaesthesia), 2022 · europepmc.orgRecommendations: light touch as the primary modality, block to T5 or higher; straight leg raise for motor block; cold and pinprick levels run several dermatomes above touch and do not predict it; Hoyle and Yentis (Anaesthesia 2015) found a trend toward touch to T5.
- 4.Failed spinal anesthesia for cesarean delivery: prevention, identification and management · Current Opinion in Anaesthesiology (Girard, Savoldelli), 2024 · pmc.ncbi.nlm.nih.govBlock testing (touch to T5, motor first), failure rates, RCoA conversion benchmarks, supplementation doses.
- 5.Use of vasopressors to manage spinal anesthesia-induced hypotension during cesarean delivery · Anesthesia and Pain Medicine (Park, Choi), 2024 · synapse.koreamed.orgSummarizes the 2018 international consensus (Kinsella et al., Anaesthesia 2018): prophylactic phenylephrine infusion, systolic at or above 90% of baseline.
- 6.SOAP Consensus Statement: Monitoring Recommendations for Prevention and Detection of Respiratory Depression Associated With Administration of Neuraxial Morphine for Cesarean Delivery Analgesia · SOAP, 2019 · soap.org
- 7.Risk factors for failed conversion of labor epidural analgesia to cesarean delivery anesthesia: a systematic review and meta-analysis of observational trials · International Journal of Obstetric Anesthesia (Bauer, Kountanis, Tsen, Greenfield, Mhyre), 2012 · scholars.duke.eduInt J Obstet Anesth 2012;21(4):294-309. 13 studies, 8,628 women; abstract read.
- 8.Comparison of lidocaine bicarbonate with fentanyl and chloroprocaine for epidural anesthesia during cesarean section · Frontiers in Pharmacology (Yu et al.), 2024 · frontiersin.orgChloroprocaine and alkalinized lidocaine fastest (Reschke 2020); chloroprocaine may antagonize epidural opioid.
- 9.Statement on Pain During Cesarean Delivery · ASA Committee on Obstetric Anesthesia, 2023 · asahq.org
Facts on this page were checked against these sources on Oct 22, 2026. Guidelines change; confirm doses against current institutional protocols.